All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional. If you are a patient or carer, please visit the Lymphoma Coalition.
The Lymphoma Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the Lymphoma Hub cannot guarantee the accuracy of translated content. The Lymphoma Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The Lymphoma Hub is an independent medical education platform, sponsored by Roche, AbbVie, BeOne, Miltenyi Biomedicine, Thermo Fisher, Nurix Therapeutics and Caribou Biosciences and supported through independent educational grants from Incyte, Bristol Myers Squibb, Pfizer and Takeda Pharmaceuticals U.S.A., Inc. Funders are allowed no direct influence on our content. The levels of sponsorship listed are reflective of the amount of funding given. View funders.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View lymphoma & CLL content recommended for you
ESMO 2016 | Selected Oral Presentations: DLBCL – HD-MTX is a highly effective prophylaxis in patients with high-risk of CNS relapse
Dr Teresa Calimeri from the San Raffaele Scientific Institute in Milan, Italy, and colleagues presented during the ESMO congress in October 2016 in Copenhagen, Denmark data from a retrospective study of 242 patients with Diffuse Large B-Cell Lymphoma (DLBCL), analyzing the effect of risk-tailored CNS prophylaxis with High-Dose Methotrexate (HD-MTX).

Patients were separated into two groups based upon their relative risk of CNS recurrence, with high-risk defined as either the involvement of specific extranodal organs and/or with an IPI score of 4–5. The prophylaxis schedule was methotrexate for 3–4 cycles intravenously with or without intrathecal chemotherapy (IT). Overall, 95 patients were in the high-risk group (39%) and 147 in the low-risk group (61%). Of the 95 patients in the high-risk group, 47 received no prophylaxis, 11 received IT alone and 36 received HD-MTX ± IT.
Patient Characteristics
| Low Risk (n = 147) | High Risk (n = 95) | |
|---|---|---|
| Median age | 66 (range 18-89) | 66 (range 24-89) |
| M/F ratio | 1.19 | 1.44 |
| PS<2 | 138 (94%) | 69 (73%) |
| B symptoms | 42 (29%) | 37 (39%) |
| Extranodal >1 | 5 (3.4%) | 42 (44%) |
| Bulky disease | 37 (25%) | 17 (18%) |
| Stage III-IV | 69 (47%) | 67 (71%) |
| IPI 0-3/4-5 | 147/- | 54/41 |
| Testis | - | 21 |
| Kidney/adrenal | - | 18 |
| Orbit | - | 6 |
| Breast | - | 1 |
| Paranasal/nasal | - | 8 |
| Skull/spine | - | 5 |
| Radiotherapy | 61 (41%) | 33 (35%) |
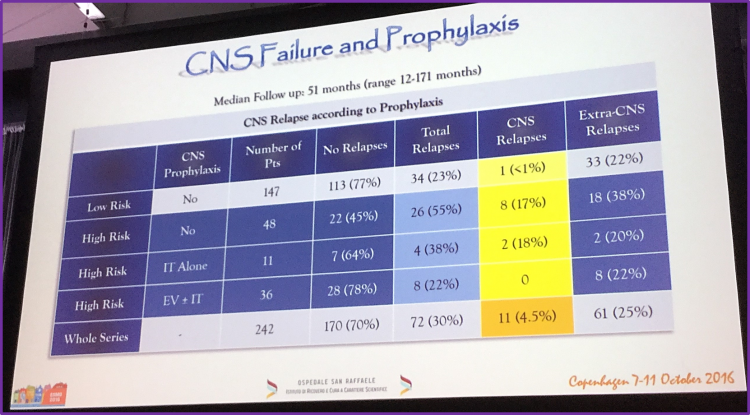
They reported that with a median follow-up time of 51 months, no one in the high-risk with HD-MTX ± IT prophylaxis group developed CNS relapse. However, two patients (18%) in the IT alone prophylaxis group, and 8 patients (17%) in the no prophylaxis group, developed CNS relapse.
Patient Outcomes - Responses After First-Line
| Low Risk (n = 147) | High Risk (n = 95) | |
|---|---|---|
| CR | 23 (84%) | 70 (74%) |
| PR | 2 (1%) | 4 (4%) |
| SD | 1 (0.7%) | 0 |
| PD | 19 (13%) | 19 (20%) |
| NA* | 2 (1.3%) | 2 (2%) |
*other causes of death: infections and heart failure
Reported three year PFS rates with HD-MTX ± IT were 81%, compared with 46% without HD-MTX. Three year OS rates were reported as 86% (HD-MTX ± IT), compared with 48% (without HD-MTX).
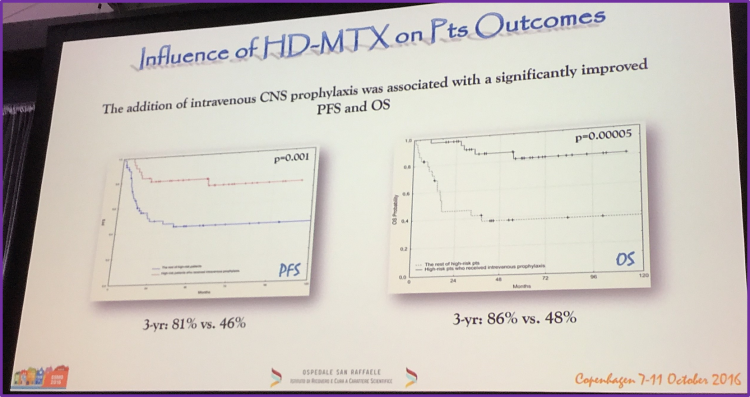
Their main conclusions at the end of this presentation were that combination prophylaxis with HD-MTX ± IT is highly effective in patients with DLBCL with high-risk of CNS relapse. They tempered this result by reminding the audience that this was a retrospective study and that the high mortality rates associated with CNS relapse could result in the reported OS effect.
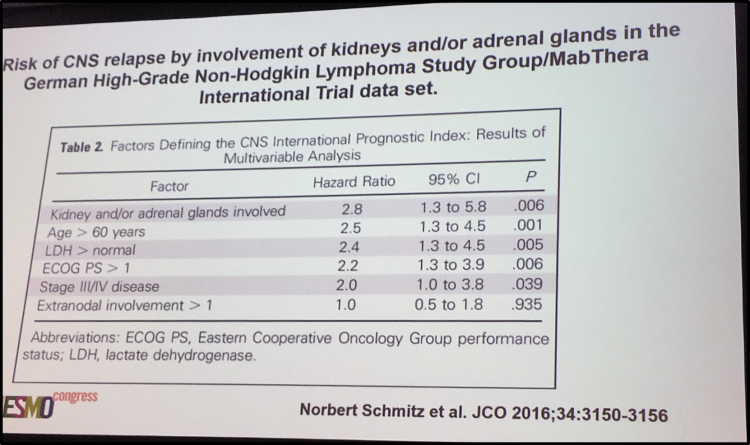
Following this presentation, a discussion session was chaired by Professor Peter Johnson from the Faculty of Medicine, University of Southampton, UK. Data was presented on the risk of CNS relapse using either the IPI score or the involvement of specific extranodal organs, the two methods by which Calimeri T. et al. defined the high-risk group.
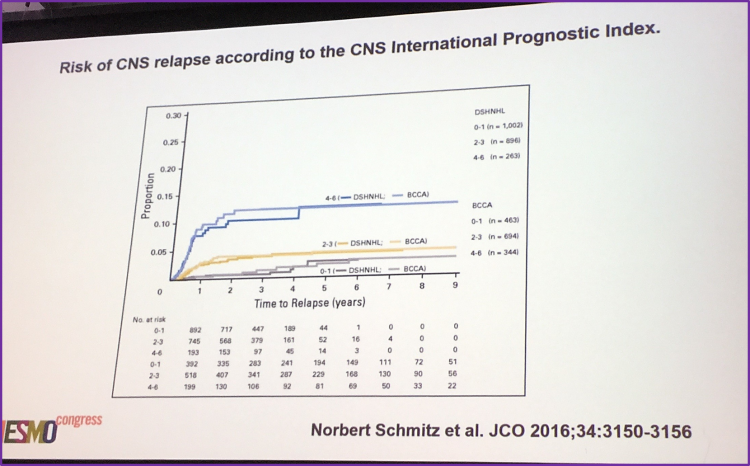
Prof. Peter Johnson then concluded by summarizing that IV MT-HDX is effective as prophylaxis in high-risk groups, the role of IT in this prophylaxis is unclear, however MT-HDX is most likely the best treatment option for patients in this group.
The talk concluded by stating that the evience remains unsatisfactory and is unlikely to improve greatly.
- Rituximab has reduced the risk of CNS recurrence
- High dose IV methotrexate is effective in high risk groups
- It is not clear whether IT prophylaxis contributes usefully
- In patients with adequate renal function and no other contraindications, high dose IV methotrexate is probably the treatment of choice
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content
This content is accurate as of the date of publication and is not updated retrospectively. Please refer to the latest available evidence, guidelines, and relevant regulatory information when making clinical decisions.
Your opinion matters
When selecting the next therapy for patients with R/R MCL after BTKi progression, what is your most important consideration?