All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional. If you are a patient or carer, please visit the Lymphoma Coalition.
The Lymphoma Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the Lymphoma Hub cannot guarantee the accuracy of translated content. The Lymphoma Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The Lymphoma Hub is an independent medical education platform, sponsored by Roche, AbbVie, BeOne, Miltenyi Biomedicine, Thermo Fisher, Nurix Therapeutics and Caribou Biosciences and supported through independent educational grants from Incyte, Bristol Myers Squibb, Pfizer and Takeda Pharmaceuticals U.S.A., Inc. Funders are allowed no direct influence on our content. The levels of sponsorship listed are reflective of the amount of funding given. View funders.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View lymphoma & CLL content recommended for you
AACR 2017 | Immune evasion in Classical Hodgkin Lymphoma
This year’s American Association for Cancer Research (AACR) annual meeting took place on 1–5 April in Washington, DC, USA. The program committee Chair was Kornelia Polyak, MD, PhD, from the Dana-Farber Cancer Institute, Boston, Massachusetts.
On Sunday 2nd April, the “RAOS02 - Immunotherapy of Lymphoid Malignancies” session was introduced by its Chair, Margaret A. Shipp, MD, also from the Dana-Farber Cancer Institute, who gave a talk on immune evasion in Classical Hodgkin Lymphoma (cHL).
The talk began by discussing Reed-Sternberg (RS) cells, which are crippled CD30+ germinal center B-cells that display genomic instability. They are found in primary cHLs with an extensive inflammatory/immune cell infiltrate.
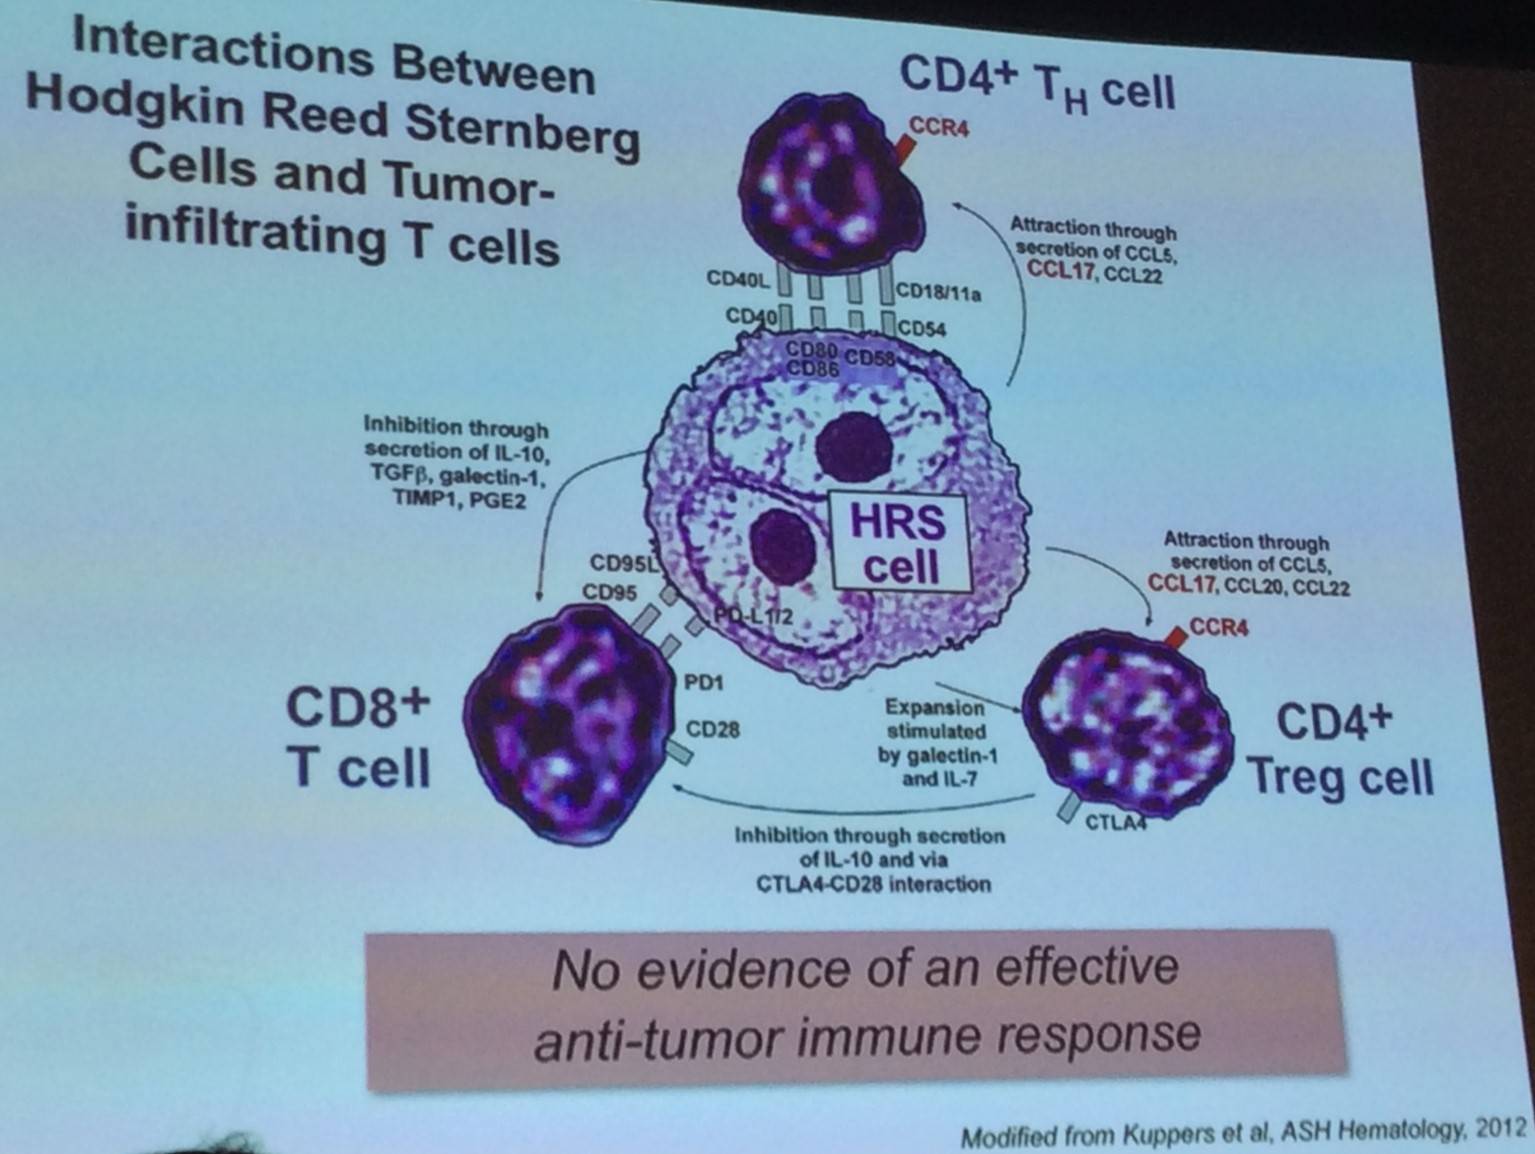
High throughput genomic assays are limited by the unique composition of cHLs. The precise incidence, nature, and prognostic impact of PD-L1/PD-L2 genetic alterations in cHL currently are unclear. The majority of newly diagnosed cHL patients display copy number alterations in PD-L1 and PD-L2, mostly copy gains and amplifications. High level alterations (amplification) can be predictive of outcome – negative standard for therapy. Therefore, does a genetic basis exist for sensitivity to PD-1 blockade?
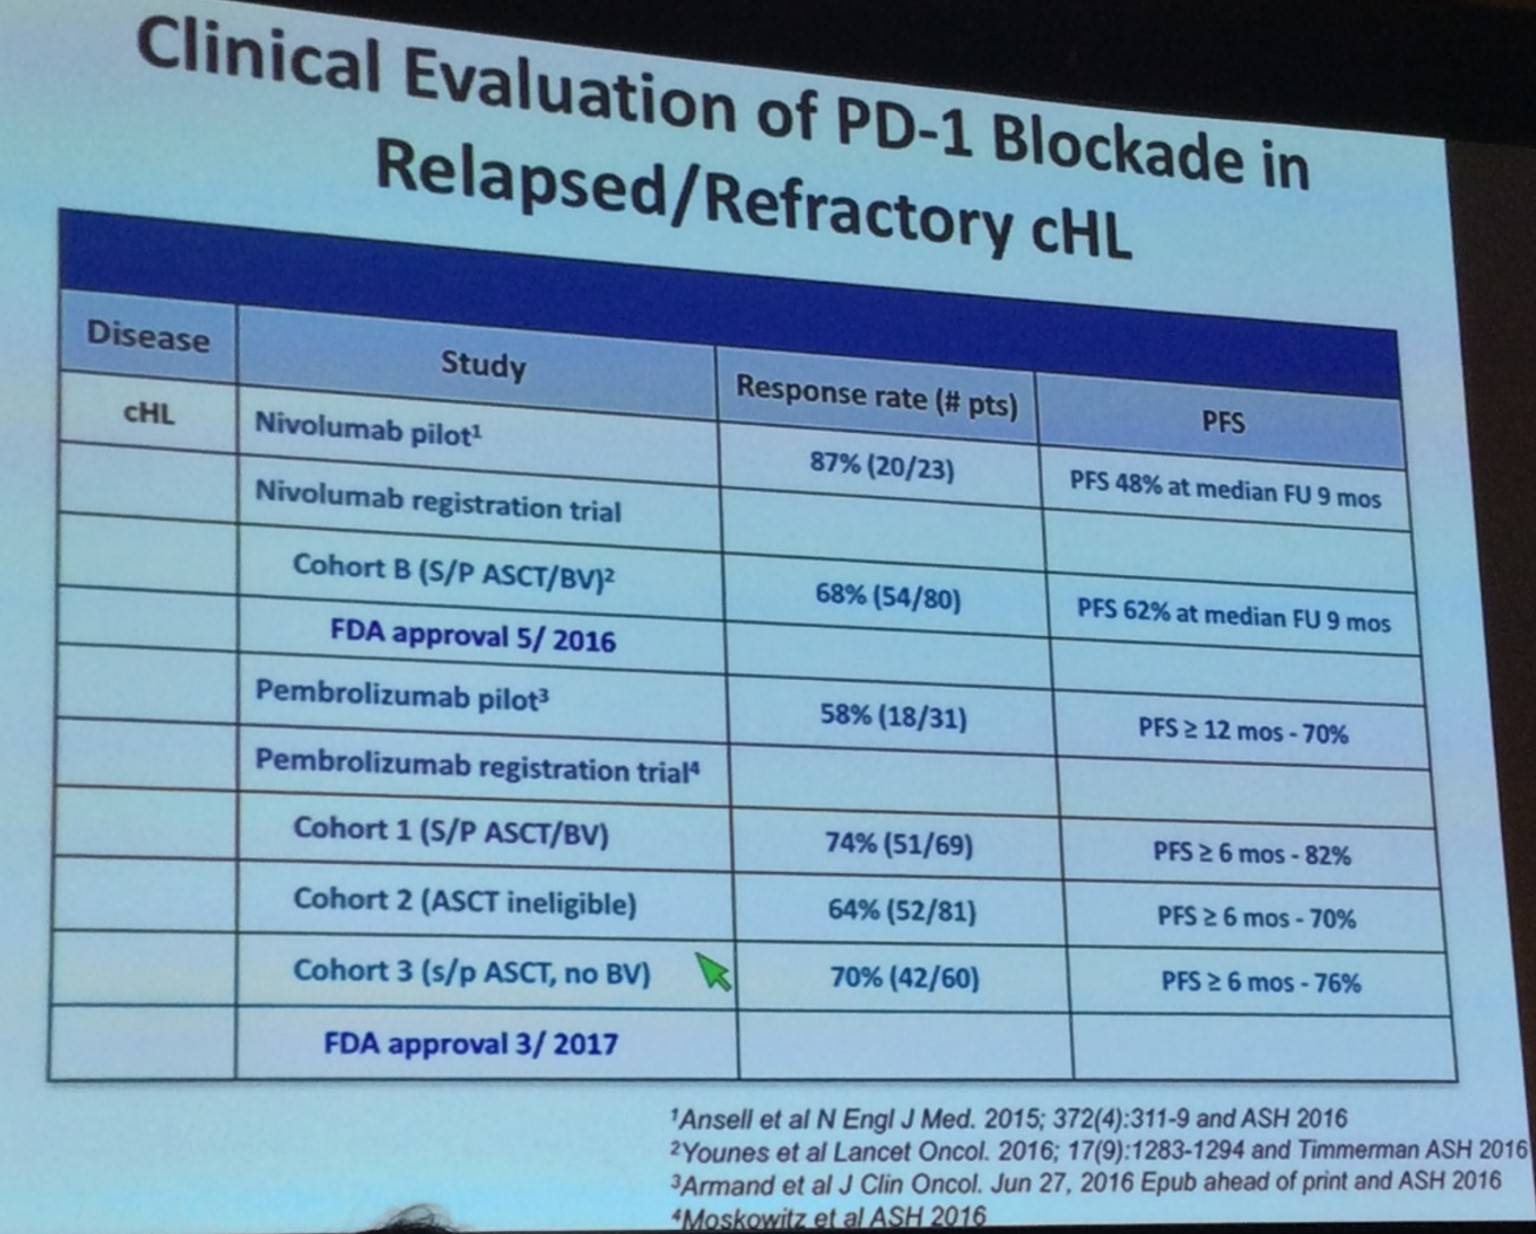
Results of the CA209-205 registration trial indicated that high levels of 9p24.1 alterations and PD-L1 expression are associated with increased sensitivity to PD-1 blockade (Younes et al. Lancet Oncol. 2016).
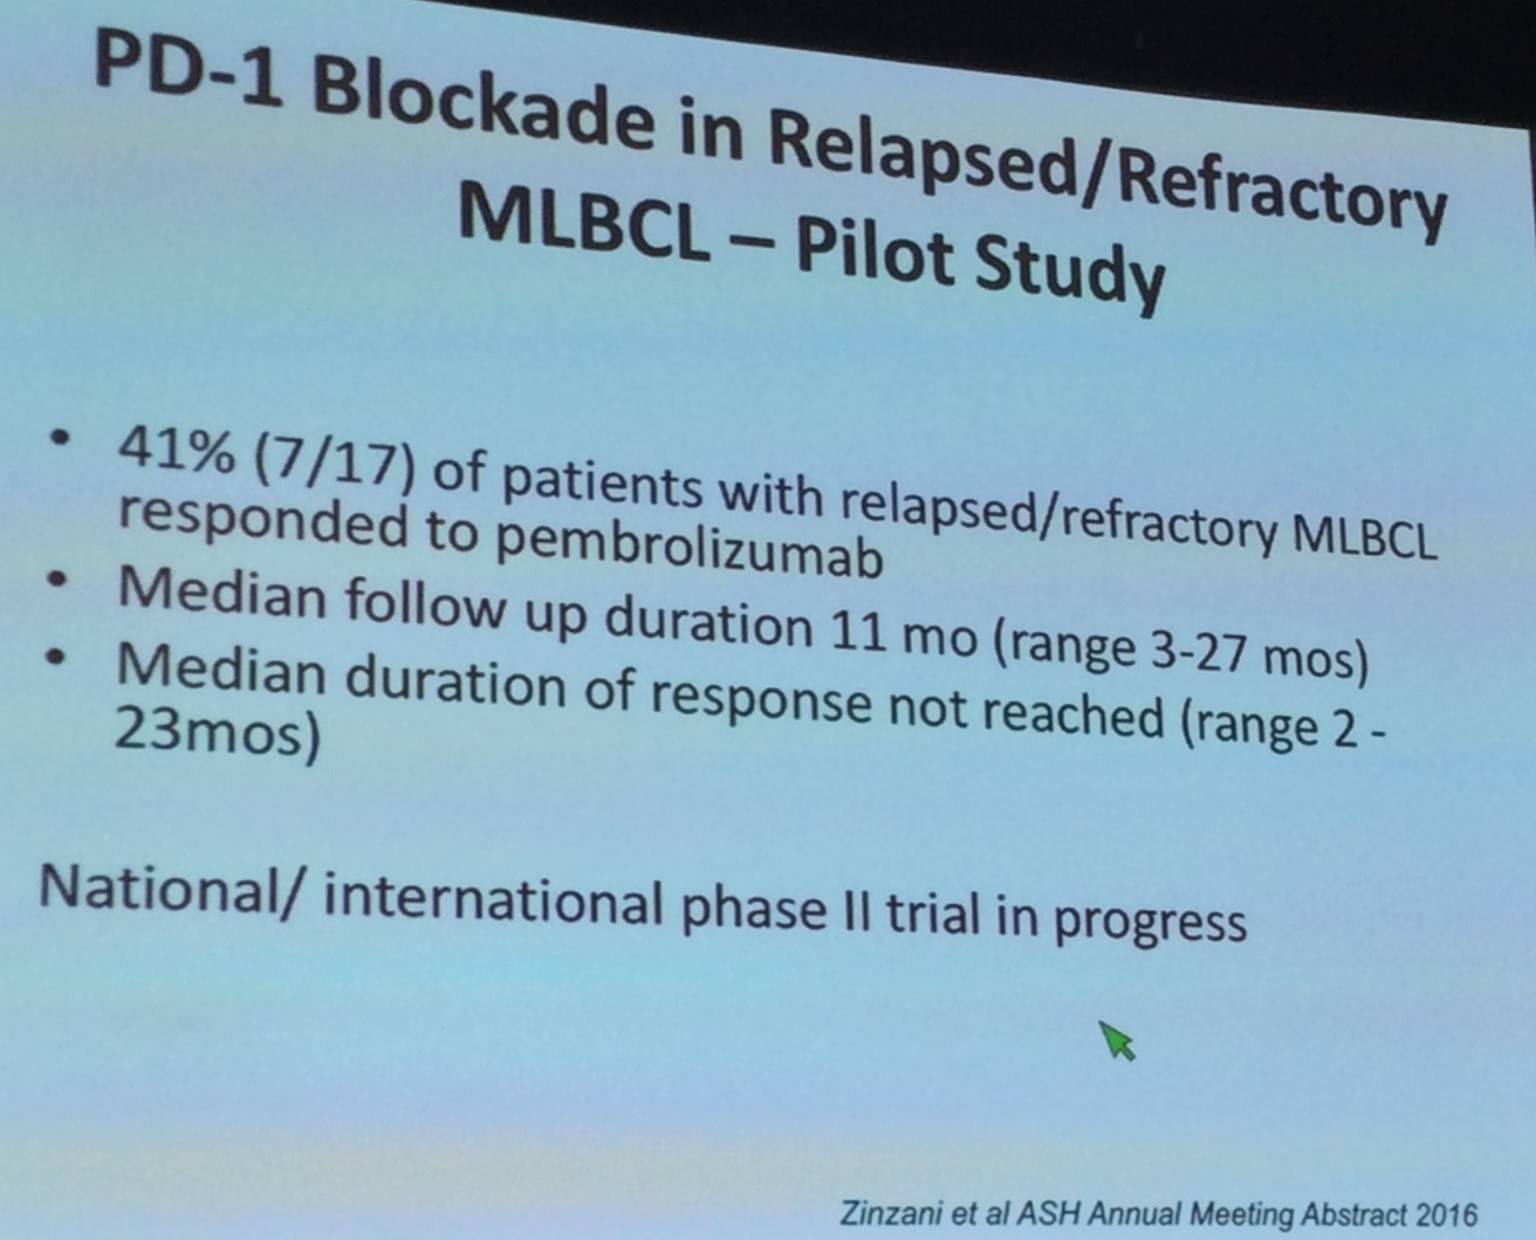
Margaret Shipp also discussed data presented by Zinzani et al. at ASH 2016 of PD-1 blockade in R/R Mediastinal Large B-Cell Lymphoma (MLBCL). 9p24.1 amplification and PD-1L overexpression has been reported in some MLBCL patients (Green et al. Blood. 2010).
The talk then focused on “immune privilege” Lymphomas:
- Take place in sites with limited normal immune responses including CNS and testes
- Large Cell Lymphomas of the CNS and testis
- Low stage (IE) but unfavorable outcome
- Certain shared molecular features
- Proposed inadequate anti-tumor immune response
- Few treatment options available; often ineffective and highly toxic
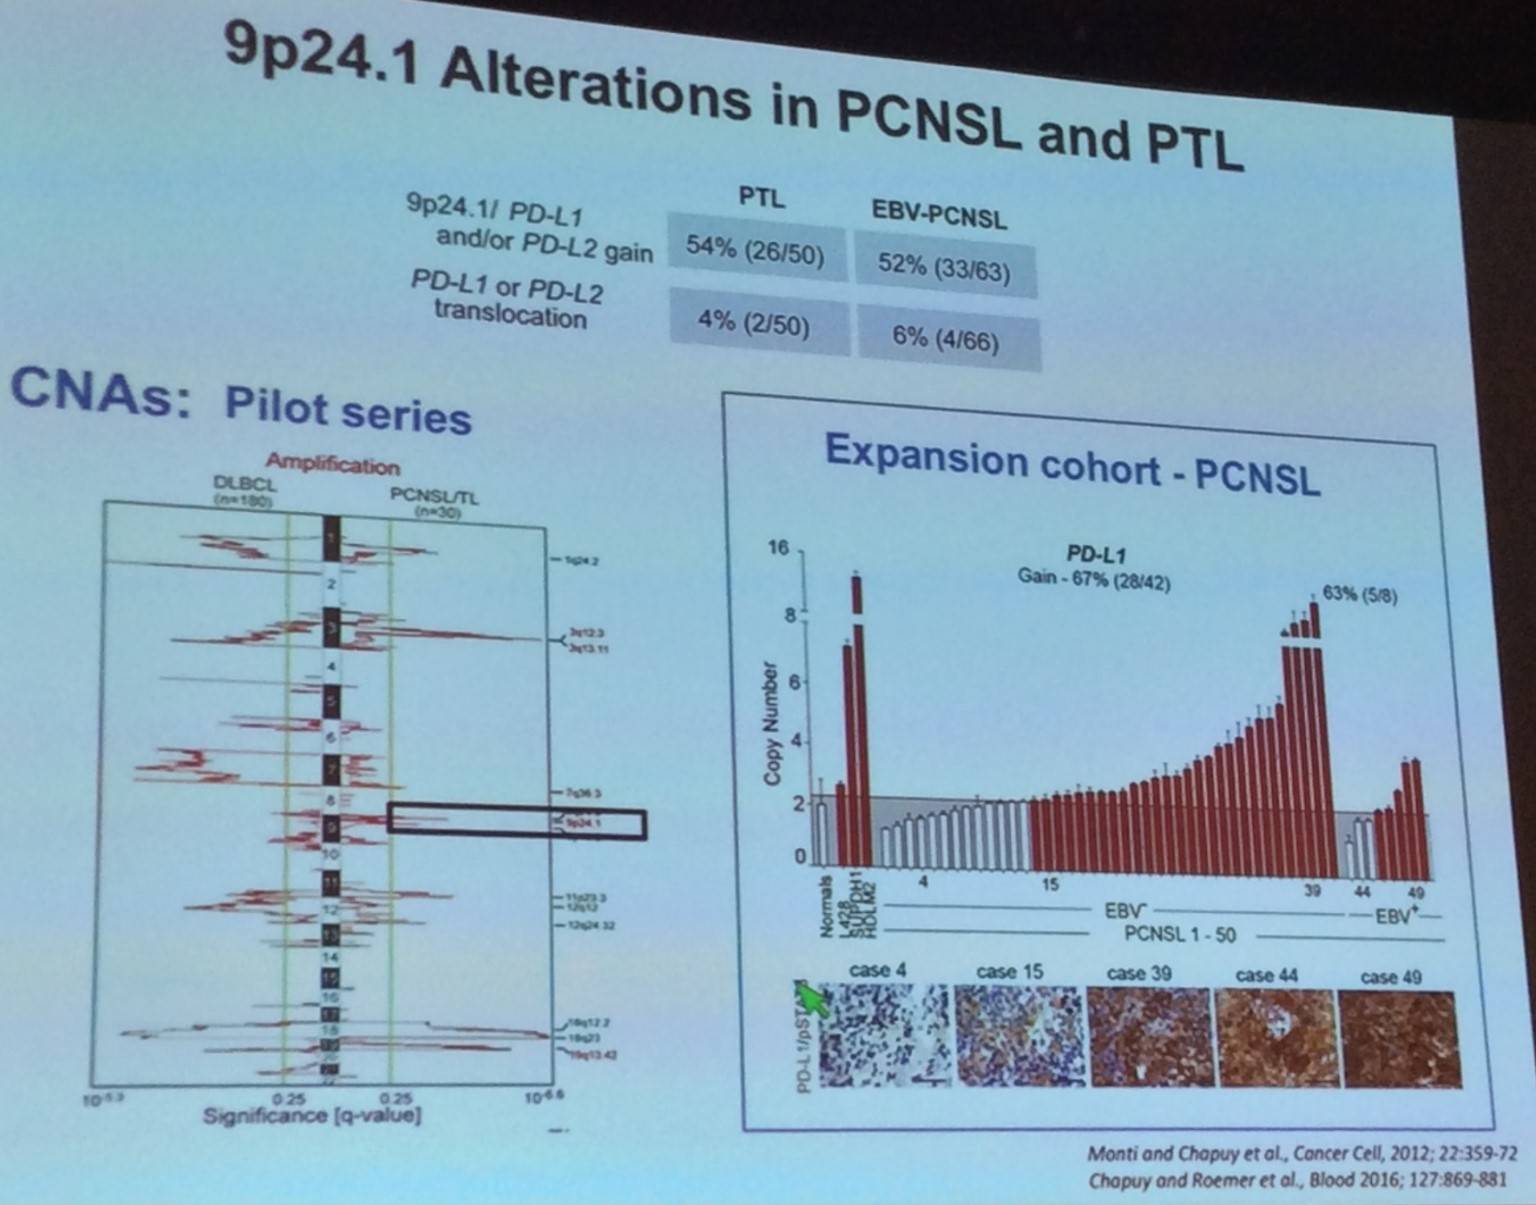
Margaret Shipp outlined findings reported by Nayak et al. during ASH 2016, exploring the use of nivolumab in Primary Central Nervous System Lymphoma (PCNSL) and Primary Testicular Lymphoma (PTL):
- R/R PCNSL (n=4), CNS relapse of PTCL (n=1)
- Clinical and radiographic responses to PD-1 blockade = 100% (5/5): 4 CRs and 1 PR
- Three patients are Progression Free (PF) at 13–17+ months; 2 patients PF at 14 and 17 months
- The CA209-746 national/international trial of nivolumab in R/R PCNSL and PTL is underway
Following this the ways in which PD-1L overexpression occurs in lymphoid malignancies was discussed:
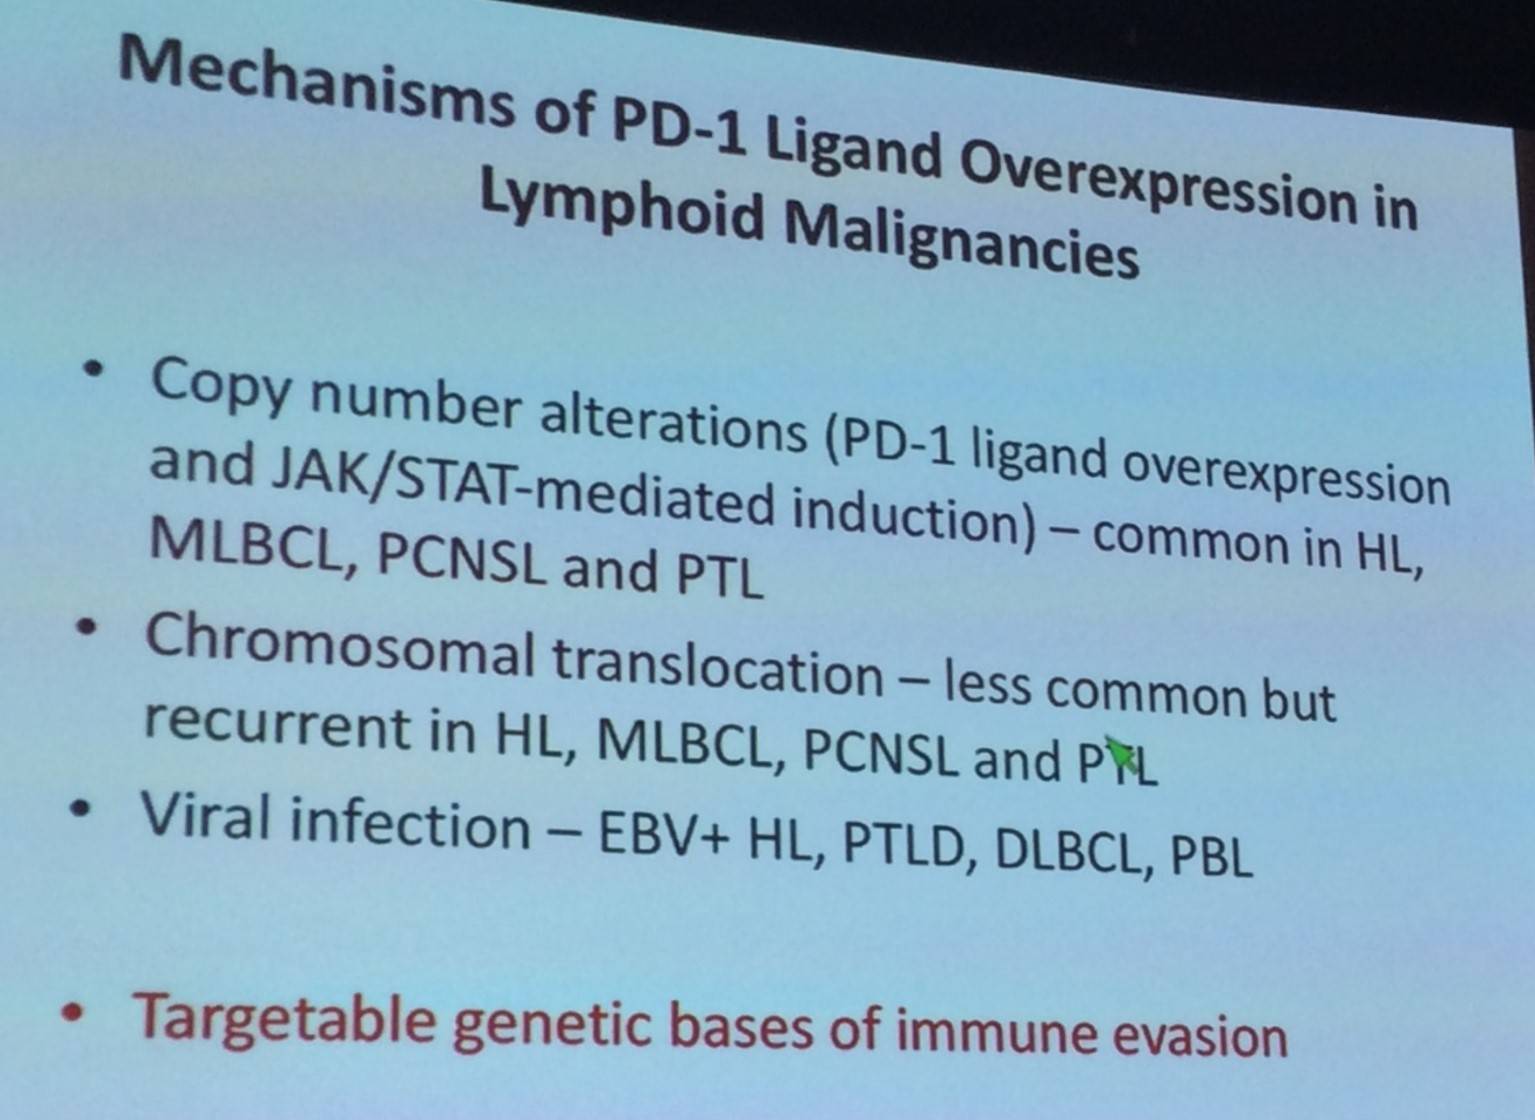
Margaret Shipp discussed findings published by Roemer et al. in Cancer Immunology Research in 2016, exploring the relationship between expression of β2M, MHC class I, and MHC class II, and 9p24.1 aberrations.
- Reduced/missing β2M/MHC class I: 85/108 (79%)
- Reduced/missing MHC class II: 72/108 (67%)
- No association found between β2M, MHC class I, and MHC class II expression and 9p24.1 genetic alterations
The talk was concluded by stating that this lack of β2M/MHC class I expression in RS cells in cHL has caused speculation regarding alternate mechanisms of PD-1 blockade in cHL.
References
- Shipp M.A. Immune evasion in Lymphoma [Presentation]. In: Proceedings of the 107th Annual Meeting of the American Association for Cancer Research; 2017 Apr 1-5; Washington, DC. Philadelphia (PA): AACR; 2017. Session nr [RAOS02].
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content
This content is accurate as of the date of publication and is not updated retrospectively. Please refer to the latest available evidence, guidelines, and relevant regulatory information when making clinical decisions.
Your opinion matters
When selecting the next therapy for patients with R/R MCL after BTKi progression, what is your most important consideration?